Blutree Orthopedic Implants
How to build a stable supply chain for orthopedic implants is not merely a purchasing question. It is a patient-care and operational challenge. Hospitals need dependable access to implants, instruments, and compatible components, often across many sizes. A missing screw or delayed tray can disrupt a scheduled procedure. Small details matter. Stability starts with visibility: teams should know which suppliers provide critical materials, where production occurs, and how long replenishment takes. This picture should include packaging, sterilization, transport, and hospital inventory, not only factory output. Numbers help, but they do not explain every delay. A supplier’s capacity can change quickly.
A practical plan combines qualified backup sources, realistic demand forecasts, clear quality controls, and traceable lot records. It also tests disruption scenarios, such as a raw-material shortage, a failed inspection, or a shipment held for review. Teams should confirm supplier capabilities and applicable requirements in each market; assumptions are risky. Communication between surgeons, procurement, quality staff, manufacturers, and logistics partners can prevent changes from becoming surprises. It is not perfect. Forecasts will miss some shifts in case mix, while extra stock can expire or tie up funds. That trade-off deserves honest review. The goal is not an unbreakable chain, which may be impossible, but one that detects problems early and recovers safely. The sections ahead examine dependency mapping, supplier assessment, quality safeguards, and measured resilience, while keeping patient needs in view.
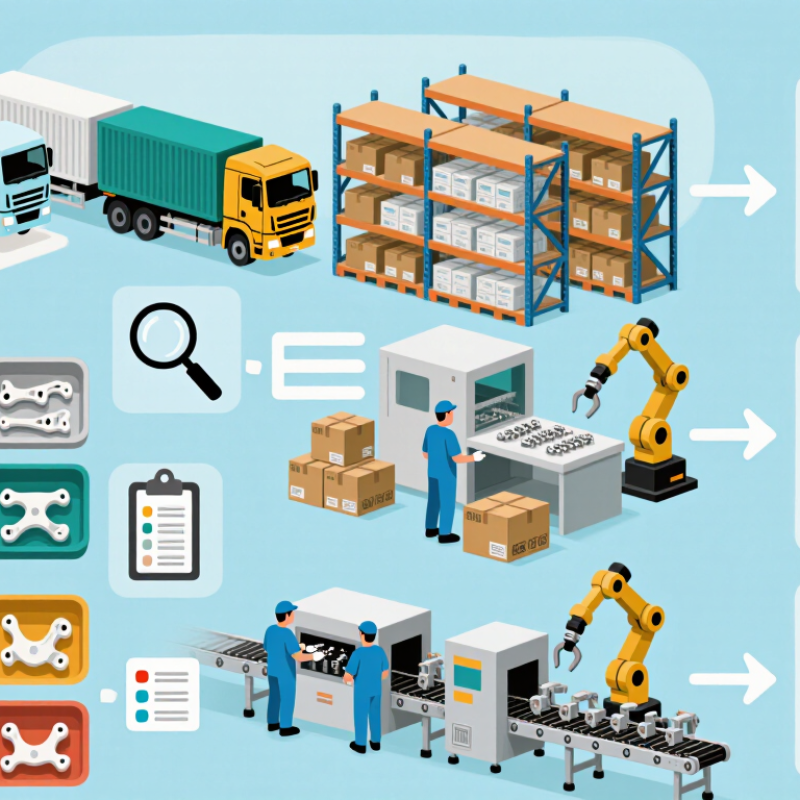
An orthopedic implant supply chain covers more than moving devices from a factory to an operating room. It includes material sourcing, design controls, production, inspection, packaging, sterilization, storage, and delivery. Each handoff matters. A small label mismatch can delay a scheduled procedure, even when the implant itself is ready.
Key components include qualified suppliers, documented manufacturing steps, and checks for dimensions, surface finish, and packaging integrity. Sterile implants need protected packaging and clear lot identification. Distribution teams must monitor stock levels, expiration dates, and delivery conditions. Hospitals also need compatible instruments, not just implants; a missing tray can disrupt a carefully planned case. Traceability links each device to its production records and destination, helping teams investigate defects or respond to a recall. Useful, but not magic.
Planning depends on reliable demand signals from hospitals and realistic production lead times. Safety stock can reduce shortages, yet excess inventory may expire or tie up resources. Simple dashboards help, though inaccurate data can make them misleading. Teams should compare forecasts with actual use and review recurring delays with suppliers and clinical staff. Even a well-designed process has gaps. A late shipment or incomplete record still deserves a careful review.
Stable orthopedic implant supply begins with a demand picture that separates procedure growth from short-term noise. The World Health Organization’s 2022 Musculoskeletal Conditions fact sheet estimates that 1.71 billion people live with musculoskeletal conditions worldwide. UN DESA’s World Population Prospects 2022 projects 1.4 billion people aged 60 or older by 2030. These figures signal long-term clinical need, not implant sales forecasts. Local procedure volumes, surgeon preferences, and case mix still matter. Forecasts still wobble.
Convert those signals into monthly plans by implant family, size, and material. Compare them with actual usage, backorders, and scheduled procedures; a small hospital may need different buffers than a high-volume center. For titanium alloy or cobalt-chromium components, track qualified suppliers, mill certificates, lot traceability, and realistic replenishment times. Include sterile packaging and sterilization capacity in the risk review, not just raw metal availability. Ask suppliers where subcomponents come from and how quickly they can recover from a disruption. Then test one scenario: a delayed material shipment, a failed inspection, or a sudden shift toward one implant size. Do not mistake a spreadsheet forecast for certainty. Small buffers help, but excess stock can expire or become unusable after design changes.
| Supply Chain Area | Relevant Data to Assess | Orthopedic-Specific Considerations | Common Risk | Practical Resilience Measure | Monitoring Metric |
|---|---|---|---|---|---|
| Demand planning | Procedure volumes, scheduled cases, historical usage, cancellations, and product-size mix | Implant demand varies by procedure type, anatomy, size, and surgeon-selected configuration. | Forecasts based only on total unit volume can miss demand for specific sizes or configurations. | Forecast by procedure and item configuration; review assumptions with clinical and operating-room teams. | Forecast error by item and size; backorders; case-related substitutions |
| Inventory and replenishment | On-hand and consigned stock, usage rate, replenishment lead time, shelf life, and stockout history | Sterile, size-specific implants and procedure sets require accurate inventory records and controlled handling. | Stockouts, expired inventory, or discrepancies between physical stock and records | Set item-level reorder points using demand variability and replenishment lead time; reconcile consigned inventory routinely. | Fill rate; inventory accuracy; expiry write-offs; days of supply by item |
| Metal materials | Material grade, mill and processing capacity, approved specifications, and lot documentation | Common implant metals include titanium alloys such as Ti-6Al-4V and cobalt-chromium-molybdenum alloys; material choice depends on device design and intended use. | Limited qualified sources, long processing routes, or material-lot variation | Qualify alternate sources where feasible and maintain traceability from material lot through finished device. | Supplier lead-time variability; material nonconformance rate; lot-document completeness |
| Polymer materials | Resin grade, material specifications, processing controls, and change notifications | Ultra-high-molecular-weight polyethylene (UHMWPE) is used in some orthopedic bearing components; its properties and performance depend on material and manufacturing controls. | Resin availability constraints or unapproved material and process changes | Review supplier change-control procedures and validate any material or process change before implementation. | Unapproved-change events; incoming inspection results; supplier delivery performance |
| Manufacturing capacity | Production capacity, equipment utilization, yield, tooling availability, and subcontractor dependencies | Precision machining, finishing, cleaning, and inspection must meet device-specific requirements. | A bottleneck process or single-site dependency can delay finished devices. | Map critical process steps and subcontractors; assess alternate capacity and recovery plans for constrained operations. | On-time delivery; production yield; work-in-process aging; recovery-plan readiness |
| Sterilization and packaging | Sterilization capacity, validated process parameters, packaging integrity, and release documentation | Sterilization method must be validated for the device and packaging. Radiation can affect some polymer properties; ethylene oxide processes require control of residuals. | Sterilizer outages, validation failures, or packaging damage may hold product from release. | Confirm validated capacity, maintain contingency plans, and monitor sterile-barrier integrity through distribution. | Sterilization queue time; batch release delays; packaging nonconformances |
| Quality and regulatory controls | Device history records, supplier qualifications, nonconformances, corrective actions, and traceability records | Implant identification and production records support traceability, investigation, and applicable regulatory obligations. | Incomplete records or quality issues can delay release and complicate field actions. | Audit critical suppliers and verify that records, lot identification, and escalation procedures are complete. | Record completeness; open corrective actions; supplier audit findings; release holds |
| Logistics and disruption response | Transit time, customs requirements, temperature or handling conditions where applicable, and route dependencies | Sterile packaged devices must be protected from damage and handled according to their labeling and validated distribution conditions. | Transport delays, border disruption, or package damage can interrupt availability. | Identify critical routes, define escalation contacts, and test alternate transport and allocation procedures. | Transit-time variation; shipment damage; disruption-response time |
Planning note: Set inventory buffers and escalation thresholds using validated lead times, demand variability, shelf life, and applicable quality-system requirements.
A stable orthopedic implant supply chain begins with evidence, not promises. Qualify suppliers against the specific materials and processes your device requires. Review machining capability, material certifications, inspection methods, and the controls used for outside processes. Ask to see a sample lot record, including heat or batch identification and measured dimensions. Paperwork is not proof.
Standardize critical manufacturing controls across approved suppliers. Define drawing revisions, measurement methods, acceptance limits, cleaning steps, and packaging requirements in clear, controlled documents. For a machined titanium component, for example, teams should agree on how key surfaces are inspected and how tool or process changes are recorded. Keep traceability intact from incoming material through finished-device release. Small details matter.
Qualification must continue after approval. Use scheduled audits, trend nonconformances, and review on-time delivery alongside quality data. Require advance notice of changes to equipment, material sources, or sub-tier suppliers, then assess their effect before implementation. A tidy audit file can still miss a recurring shop-floor issue. That happens. Leave room for practical judgment: risk-based checks may need to increase when a supplier changes a process or shows unstable results. Document decisions, owners, and follow-up dates, so corrective actions do not disappear between meetings.
A stable orthopedic implant supply chain starts with accurate inventory records. Track demand by procedure type, size, configuration, and expiration date. Keep a practical buffer for frequently used items, but avoid treating every product alike. Weekly reviews of open orders, usage, and approaching expirations can reveal gaps before they affect a scheduled procedure. Small checks matter.
Traceability should link each implant’s identifier and lot or serial number to its receipt, storage location, pick, and shipment. At dispatch, match labels against the order and inspect the packaging. If a record or package looks wrong, hold the unit while staff verify the details. Even careful systems have weak spots: an entry may be late or duplicated. Paper backups can help during outages, though they can also create conflicting records.
Distribution depends on realistic lead times, clear handoffs, and an escalation plan for delays. Use protective shipping methods and follow the product’s specified handling and storage conditions. For urgent requests, confirm available sizes and delivery windows before promising arrival. Review stockouts and late deliveries each month, then adjust reorder points using actual usage. Perfect data is unlikely. Consistent correction is more useful.
Manage inventory, traceability, and distribution with clear, measurable operational KPIs.
Illustrative planning data, not an industry benchmark. Track these measures together to spot fulfillment or traceability gaps and guide replenishment planning.
Orthopedic implant continuity depends on measurable signals, not reassuring supplier promises. Track on-time, in-full deliveries, lead-time variation, backorders, and quality holds by implant family. A weekly view can expose a pattern: a tray arrives late, a sterilization release slips, or a hospital case needs a substitute size. Record the cause, owner, and recovery date. Keep the data visible to clinical, procurement, and operations teams.
The McKinsey Global Institute’s 2020 supply-chain analysis estimated that companies face a month-long disruption, on average, every 3.7 years. That finding covers global supply chains, not orthopedic implants alone. Still relevant. Set reorder triggers using actual usage and replenishment times, then test them against demand spikes and supplier delays. Maintain qualified alternatives for critical components, and verify their capacity before an emergency. A scorecard can look green while one packaging or sterilization source remains a single point of failure. No metric catches every weak link. Review supplier risks regularly, and use tabletop exercises to test who acts when a shipment misses its window. Some thresholds will be imperfect; revise them when real delivery data contradicts the plan.
Check machining capability, material certifications, inspection methods, and controls for outside processes. Request a sample lot record with batch identification and measured dimensions. Paperwork alone is not proof.
Define drawing revisions, measurement methods, acceptance limits, cleaning steps, and packaging requirements. For a titanium component, agree on how key surfaces are inspected. Record process changes clearly.
Schedule audits, track recurring nonconformances, and review delivery performance alongside quality data. Ask suppliers to report equipment, material-source, and sub-tier changes in advance. Follow up.
Track on-time, in-full delivery, lead-time variation, backorders, and quality holds by implant family. Record each delay’s cause, owner, and recovery date. Keep the view accessible.
Review performance regularly across clinical, procurement, and operations teams. A late tray or delayed sterilization release may signal a wider issue. One metric may miss it.
Base triggers on actual usage and replenishment times. Test them against demand spikes and supplier delays. Real data may expose weak assumptions.
Alternatives can help protect supply continuity, but confirm their capacity before an emergency. Check packaging and sterilization sources too; either may become a single point of failure.
Use tabletop exercises to decide who acts when a shipment misses its window. Document decisions, owners, and follow-up dates. Some thresholds will need revision.
How to build a stable supply chain for orthopedic implants begins with understanding the full process, from demand planning and material sourcing to manufacturing, storage, and delivery. Accurate forecasts help organizations prepare for changing clinical needs, while careful assessment of material availability, lead times, and potential disruptions can reveal vulnerabilities before they affect supply.
A resilient approach also depends on qualifying suppliers, maintaining consistent manufacturing controls, and keeping clear records for inventory and product traceability. Appropriate stock levels and coordinated distribution help ensure implants are available when needed without creating unnecessary excess. By regularly reviewing supplier performance, delivery reliability, quality indicators, and emerging risks, organizations can address problems early and strengthen continuity across the supply chain.
